What the anion gap measures
The anion gap is a calculated value that helps estimate the balance between measured electrolytes in the blood and the unmeasured ions that are not directly shown on a serum chemistry panel. It is often used as a diagnostic marker for acid-associated problems and other metabolic abnormality patterns. In simple terms, it helps clinicians look for clues about whether the body’s electroneutrality is being maintained as expected.
Blood contains positively charged particles, called cations, and negatively charged particles, called anions. The major measured cations and anions on routine serum electrolytes testing include sodium, chloride, and bicarbonate. Because the body must stay electrically balanced, any difference between the main measured ions can suggest the presence of unmeasured anions or other shifts in plasma chemistry. That difference is what the anion gap reflects.
The clinical significance of the anion gap is not that it diagnoses a single disease. Instead, it provides a framework for interpretation of lab results in the setting of illness, especially when evaluating acid-base disorder patterns. A high or low result may point to a broad range of causes, so the number must always be considered in diagnostic context with the patient’s symptoms and other blood chemistry findings.
Why Na is a component of the formula
Sodium is used in the anion gap formula because it is the dominant measured cation in extracellular fluid and a key contributor to plasma charge balance. In standard lab practice, the usual formula is:
anion gap = sodium - (chloride + bicarbonate)Some versions of the formula may include potassium, but sodium is the key analyte because it represents most of the measured positive charge. The formula sets the main cation, sodium, against the main measured anions, chloride and bicarbonate. The difference offers an estimate of the amount of unmeasured negatively charged substances in the blood.
This is where the concept of electroneutrality becomes important. The body’s fluids must remain electrically balanced, so the total positive and negative charges should generally match. Since not all ions are directly measured, the anion gap uses sodium as the basis for the calculation. Without sodium, there would be no easy way to estimate the gap between measured cations and measured anions.
The role of bicarbonate is also critical. When bicarbonate decreases, as it often does in metabolic acidosis, the calculated gap may rise if the lost bicarbonate is replaced by unmeasured acids. This makes the formula helpful for identifying certain metabolic disturbance patterns that are using osmolar gap with anion gap not obvious from sodium alone.
How an Anion Gap Calculator uses sodium values
An Anion Gap Calculator is a useful tool that applies the formula automatically with your serum sodium, serum chloride, and serum bicarbonate values. The calculator carries out the calculation rapidly and lowers the chance of arithmetic mistakes during lab interpretation. It is especially helpful when reviewing many lab values in a brief time or when comparing repeated results over time.
The calculator’s output shows a gap calculation based on standard serum chemistry data. Because sodium is the primary starting point, even slight changes in serum sodium can influence the final number. However, the effect is best understood in combination with chloride and bicarbonate rather than sodium by itself. A change in one analyte may shift the result while the underlying physiology remains stable or changes in the opposite direction.
For example, if sodium remains unchanged but bicarbonate falls, the calculated gap may rise. If sodium falls or rises markedly, the absolute gap may also shift, but interpretation depends on whether the change reflects an actual acid-base disturbance, dilution, water balance changes, or another clinical factor. That is why an Anion Gap Calculator is an estimate tool, not a standalone diagnosis.
In practice, the calculator helps arrange lab results into a pattern that guides clinical reasoning. It can draw attention to a possible abnormal result, but the next step is always to interpret the number in relation to the overall electrolyte panel, symptoms, and other findings.
How increased sodium vs low sodium can indicate about the anion gap
Variations in sodium levels may affect the anion gap in ways that are that are medically important but not always easy to interpret. In hypernatremia, sodium is high, which can shift the calculated value upward. In hyponatremia, sodium is reduced, which can lower the result. Still, the relationship is not purely numerical; it is also tied to water balance, plasma concentration, and the broader state of acid-base balance.
High sodium does not always mean a high anion gap disorder is present. A patient can have hypernatremia from fluid loss or water loss without a main acid-base problem. Likewise, low sodium may be due to excess water relative to solute, endocrine issues, kidney-related problems, or other causes that do not directly produce a high anion gap or low anion gap. The key is to avoid treating the anion gap as a sodium-only metric.
Serum osmolality can be useful to put sodium changes into better view. Because sodium strongly influences osmolality, marked shifts in sodium may indicate a broader disturbance in fluid distribution. That disturbance may coexist with an acid-base issue, but it does not confirm one. The best interpretation brings together sodium with chloride, bicarbonate, and the patient’s overall status.
When sodium is off, it can also affect the perceived severity of an acid-base disorder. A calculated gap may appear higher or reduced than expected because the baseline concentration of the dominant cation has changed. For that reason, a careful reviewer should ask whether the sodium abnormality is driving the result, masking another issue, or simply occurring alongside it.
Main causes of a high anion gap
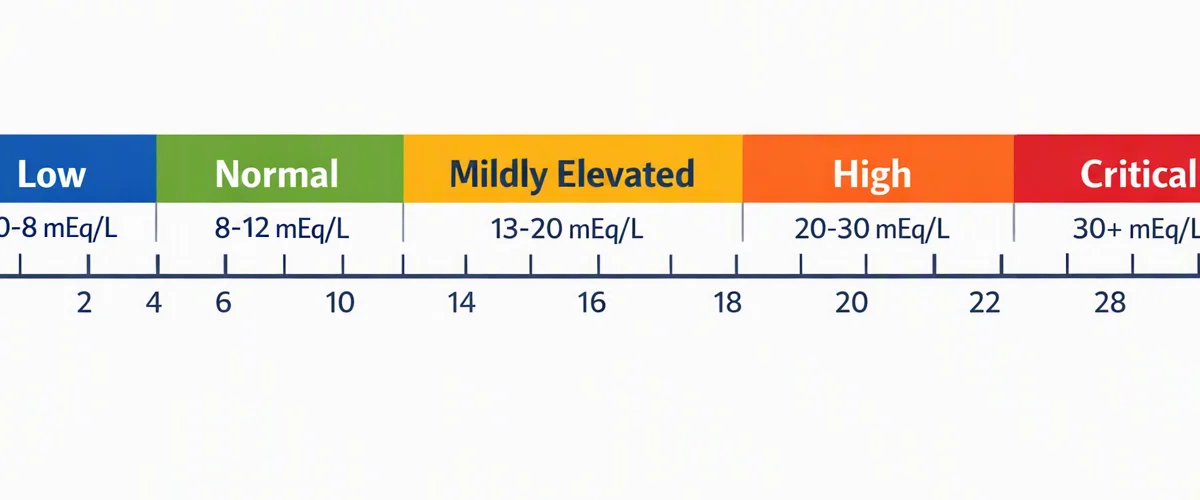
A high anion gap usually suggests that unmeasured acids are present in excess. This finding is frequently seen in acid buildup, where bicarbonate is consumed as it neutralizes acid. Because bicarbonate falls, the calculation leaves a wider difference between sodium and the measured anions.
One common cause is excess lactate, which occurs when lactate rises faster than the body can clear it. Lactate is an unmeasured anion in standard routine labs, so it can raise the gap. This may happen in low blood flow, poor tissue oxygen delivery, severe illness, or other conditions that alter metabolism and perfusion.
Another important cause is ketone-related acidosis. In this condition, ketone bodies accumulate and contribute unmeasured anions. It is often associated with diabetes, prolonged fasting, or alcohol-related metabolic changes. The rise in unmeasured acids alters the blood chemistry pattern and can produce a distinctly elevated gap.
Uremia from impaired kidney clearance is also a classic contributor. When renal function declines significantly, acids and other solutes that should be excreted can build up. This affects the blood’s balance of measured and unmeasured components, making the anion gap a valuable indicator in the broader assessment of kidney-related metabolic disturbance.
Other contributors can include toxins, severe illness, anion gap in chronic kidney disease and mixed disorders. Still, the core idea remains the same: a high gap usually means the body has built up acids or kept unmeasured anions that are not captured directly in the routine electrolyte values.
When a typical anion gap can still be misinterpreted
A routine result does not always mean the electrolyte picture is truly unchanged. A number of factors can make the anion gap look reassuring even when a clinically important problem is present. One major factor is albumin, the most abundant negatively charged protein in plasma. Because albumin contributes substantially to the usual gap, low albumin can obscure an elevated gap state.
This is why clinicians sometimes use a corrected anion gap. The correction accounts for hypoalbuminemia so the result better reflects the real burden of unmeasured anions. Without this step, a patient with low albumin may appear have a normal gap even though a significant acid-base disorder is present underneath.
Lab error is another concern. Sample handling problems, measurement variability, or reporting mistakes can alter sodium, chloride, or bicarbonate values enough to affect the result. A suspicious number should always be rechecked against the full lab record and the clinical picture.
The chloride shift can also confuse interpretation. If chloride rises to balance out another change, the calculated gap may stay within the expected reference range even when a significant process is occurring. In other words, the body may maintain apparent balance on paper while still undergoing a real metabolic change.
For these reasons, a normal gap should be viewed as one clue, not the final answer. It can be especially misleading in mixed disorders, low albumin states, or cases where fluid shifts alter measured electrolyte concentrations.
How to interpret findings in the proper setting
The most precise clinical interpretation of an anion gap result is based on combining it with the rest of the patient’s data. Sodium, chloride, and bicarbonate tell only a portion of the story. Additional information such as potassium, renal function, symptoms, medications, and the presence of illness all affect the meaning of the number.
An arterial blood gas is especially valuable when an acid-base problem is suspected. It gives information about pH, carbon dioxide, and compensatory changes that can help determine whether the patient has metabolic acidosis, respiratory issues, or a mixed disorder. In many cases, the anion gap is only one piece of the larger acid-base puzzle.
It is also important to assess whether compensatory changes make physiologic sense. The body often responds to a metabolic disturbance with predictable respiratory or renal adjustments, but these responses may be incomplete or masked by another condition. That is why the calculated gap should be interpreted alongside symptoms, examination findings, and the overall serum electrolytes pattern.
In everyday practice, the best approach is to think in stages:
- Verify whether sodium, chloride, and bicarbonate are abnormal. Determine whether the calculated gap is high, normal, or low. Consider albumin and consider a corrected anion gap when needed. Assess for renal impairment, lactic acidosis, ketoacidosis, or uremia. Support the result with broader clinical context and, when appropriate, arterial blood gas testing.
This stepwise approach strengthens lab interpretation and reduces the risk of overreading a single abnormal result. An abnormal result can be highly informative, but only when viewed as part of a complete diagnostic context.
Frequently asked questions about sodium and the anion gap
What’s the purpose of sodium in the anion gap?
Sodium is the main checked cation used in the anion gap formula. It offers the baseline for the calculation, which matches sodium against chloride and bicarbonate to calculate the quantity of hidden anions in plasma. Without sodium, the calculation would not work as a reliable screening tool for electrolyte stability and acid-base issues.
Why does the anion gap formula include sodium?
The formula features sodium because it is the main cationic analyte in routine serum electrolytes analysis. As the body must maintain electroneutrality, sodium is used as the anchor for assessing measured cations with measured anions. This can help reveal hidden shifts in blood chemistry that may point to metabolic disruption.
Can low sodium affect the anion gap result?
Indeed. Hyponatremia may reduce the final result because sodium is the main starting value in the formula. But the meaning of that change depends on the complete patient picture, including chloride, bicarbonate, serum osmolality, and whether there is a real acid-base issue. Hyponatremia alone does not determine the cause.
Can a normal anion gap exclude acid-base problems?
No. A regular result does not exclude all acid-base disorder patterns. Problems can be masked by hypoalbuminemia, lab error, a chloride shift, or mixed disorders. For this reason a normal value should be interpreted with the rest of the electrolyte panel, the patient’s symptoms, and any arterial blood gas results when available.
How does an Anion Gap Calculator assist in interpreting lab results?
An Anion Gap Calculator rapidly calculates the anion gap calculation using serum sodium, chloride, and bicarbonate. It aids arrange lab values, identify a possible increased anion gap or decreased anion gap, and facilitate faster lab interpretation. However, it does not replace clinical interpretation, since albumin, renal function, and the broader diagnostic context still matter.