Understanding an Anion Gap Calculator?
An anion gap calculator is an internet-based tool that helps estimate the anion gap from routine electrolytes measured on a blood chemistry panel. It is used as a fast diagnostic aid in evaluating acid-base balance and potential electrolyte imbalance. In plain terms, the calculator compares recorded positively charged and negatively charged particles in the blood to identify whether there may be an anion deficit that suggests a metabolic disturbance.
The result is useful because the body normally maintains electroneutrality, meaning total positive charge and total negative charge stay tightly balanced. When the balance alters, the anion gap can go up or remain normal depending on the cause. That makes the calculator a useful tool for checking and result comparison, especially when reviewing serum chemistry or other lab values with a clinician.
An online calculator does not make a diagnosis by itself. Instead, it gives a calculation that supports interpretation of possible acid-base disorder patterns. Used properly, it can help you understand whether the result fits a standard anion gap pattern or a high anion gap pattern and whether more medical review is needed.
Which Measurements Do You Type Into the Calculator?
Most anion gap calculators ask for four standard lab values: sodium, chloride, bicarbonate, and in some cases potassium. These are usually found on a blood chemistry panel or comprehensive metabolic panel, often listed in millimoles per liter.
For the typical workflow, you will input:
- Sodium level Chloride concentration Bicarbonate value Potassium concentration, if the calculator includes it
Many calculators are designed to work with sodium, chloride, and bicarbonate alone. Other tools include potassium because it slightly changes the formula. Always check the input fields and use the exact lab values from your report rather than rough guesses.
It also helps to confirm that the numbers come from the same blood draw. Mixing lab values from different times can distort the calculation and lead to an abnormal result that does not reflect the current clinical context.
How the Anion Gap Is Calculated
The utility uses a straightforward formula from observed electrolyte values. A common version is:
Anion gap = sodium − chloride − bicarbonate
If potassium is added, the formula may be:
Anion gap = sodium + potassium − chloride − bicarbonate
This formula reflects the principle of electroneutrality. Since not all blood ions are directly tested, the anion gap estimates the gap between unmeasured anions and unmeasured cations. That is why it can be valuable in identifying certain sources of metabolic acidosis and other metabolic abnormalities.
Albumin matters because it is a important unmeasured anion in the blood. If albumin is low, the measured anion gap may appear lower than expected. In that instance, the raw calculation may lower the true gap, which is why some clinicians use a corrected anion gap.
Even though the math is straightforward, the interpretation is less direct. The number is most useful alongside other lab values, the reference interval used by the lab, and the patient’s overall acid-base balance.
How to Understand the Result
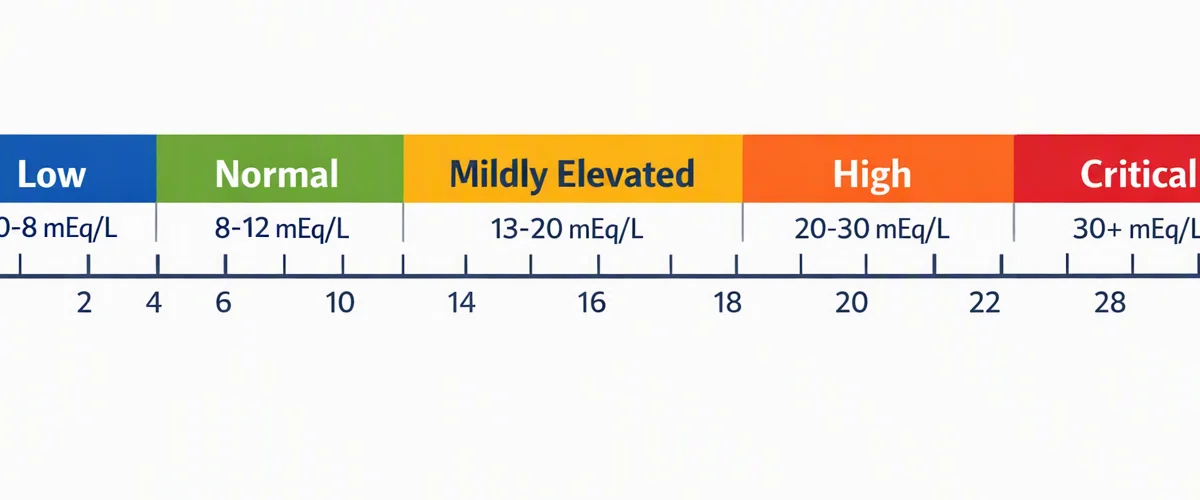
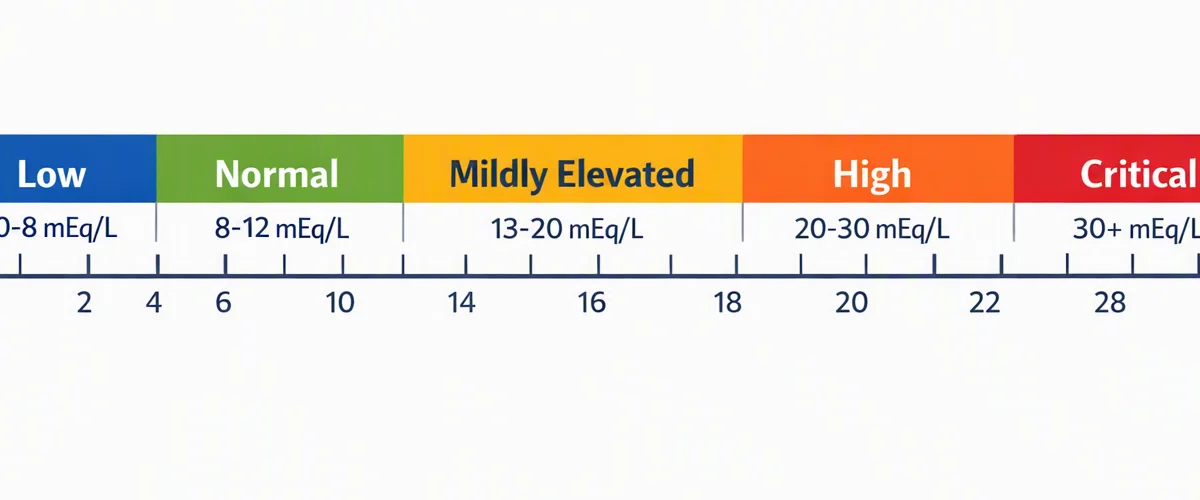
After the calculation is finished, the next step is interpretation. A normal anion gap usually suggests that the difference between measured cations and anions is inside the expected reference range. A high anion gap indicates extra unmeasured acids may be present and may be consistent with metabolic acidosis.
Interpretation depends on the lab’s reference range, because the normal interval can differ a little by method and analyzer. In many cases, a result in the typical range is reassuring, but it does not rule out all acid-base disorders. Likewise, a high value does not determine the exact cause on its own.
Here is the practical way to think about the output:
- Normal anion gap: commonly found when acid loss is balanced by chloride gain or when the underlying problem is not driven by unmeasured acids. High anion gap: may indicate accumulation of acids and a more specific metabolic process. Result comparison: the number should be compared with serum albumin, bicarbonate, and the broader clinical picture.
To put it another way, the calculator is a fast screening tool, but interpretation is a diagnostic aid rather than a final answer. If the result suggests metabolic acidosis or another abnormal result, the next step is usually a medical review of the underlying cause.
Common Causes of a High Anion Gap
A high anion gap usually indicates excess acids in the body. This pattern is often seen in metabolic acidosis, where the bicarbonate concentration drops as it buffers acid. Several common causes should be evaluated during interpretation.
Lactic acidosis can occur when tissues do not get enough oxygen or when lactate production increases. This can happen in severe illness, poor circulation, or other metabolic stress. Because lactate is an unmeasured anion, it raises the gap.
Ketoacidosis is another common cause. It can happen with https://anion-gap-chart316.cavandoragh.org/how-to-work-with-an-anion-gap-calculator-in-acid-base-analysis diabetes, prolonged fasting, or alcohol-related metabolic changes. Ketone bodies add to the acid load and increase the anion gap.
Renal failure can also cause a high result because the kidneys are less able to remove acids effectively. As acid accumulates, the anion gap may rise.
Toxic alcohols, including certain ingestions that produce harmful metabolites, are a classic cause of high-gap metabolic acidosis. These situations are medical emergencies and require urgent assessment.
Other possible causes exist, but these are among the most important to know when using an online calculator. A high result should always be reviewed in the context of symptoms, history, and other lab values.
Typical Causes of a normal anion gap
A normal anion gap doesn't mean the entire body is normal, but it does suggest that the reason of acidosis, if present, may involve a separate mechanism. One frequent cause is diarrhea, which can lead to loss of bicarbonate from the gastrointestinal tract. The body often responds with a chloride rise, so the gap stays within the reference interval.
Renal tubular acidosis is another important cause. In this condition, the kidneys do not process acid and bicarbonate properly, which can produce a normal anion gap metabolic acidosis pattern.
Bicarbonate loss from the gut or kidneys often creates this same pattern. The body may not retain extra unmeasured acids, so the anion gap remains in range even though acid-base balance is disturbed.
When the calculator shows a normal number, it is still important to review symptoms and the rest of the blood chemistry panel. A normal gap can coexist with a real acid-base disorder, especially if there is a mixed disturbance or a changing clinical picture.
When to Correct for Albumin
Correcting for albumin is important when hypoalbuminemia is present. Since serum albumin is a major unmeasured anion, low levels can reduce the measured anion gap and mask a clinically meaningful elevation. In that case, a corrected anion gap gives a more accurate estimate of the underlying acid-base state.
Numerous online calculators include an albumin adjustment field. If yours does, enter the serum albumin value exactly as reported by the lab. The calculator then applies an adjustment to the original result. This is especially helpful when the uncorrected number seems normal but the clinical context suggests metabolic acidosis or another abnormal result.
Albumin adjustment is not needed in every case. If albumin is normal and the result aligns with the rest of the labs, a corrected anion gap may offer minimal added value. But if albumin is low, the adjustment can reduce underestimation and support result interpretation.
For practical use, think of albumin correction as a refinement step, not a separate diagnosis. It helps the calculation match the patient’s true metabolic state more closely.
Step-by-Step: How to Operate an Online Tool
Using an online anion gap calculator is easy if you apply a steady workflow. Start by gathering the lab values from the identical blood chemistry panel. Check the units and make sure you have the proper lab values before typing in anything.
Here is a simple stepwise process:
- Access the anion gap calculator. Identify the input fields for sodium, chloride, and bicarbonate. Enter potassium only if the calculator requests it or includes it as an option. If available, enter serum albumin for an albumin correction. Confirm that the numbers match the report exactly. Perform the calculation and check the displayed result. Match the result with the calculator’s reference range or reference interval. Check the result interpretation if the tool provides one.
The ideal workflow is to move carefully at the input stage. Most errors happen because a value was entered wrong, copied from the wrong report, or entered with the wrong concentration. A careful check improves the quality of the calculation and the usefulness of the interpretation.
If the calculator gives a result that appears off, review the electrolyte inputs, the reference range, and the albumin value before drawing conclusions. This simple verification step can prevent unnecessary concern and support better clinical context.
Restrictions and When to Request Medical Review
Although an online calculator is useful, it has clear limitations. A single number cannot account for every clinical context, and the same result can mean different things depending on symptoms, medications, and other lab findings. The calculator is a screening tool, not a complete diagnosis.
Lab error is one reason to recheck an unexpected result. Mislabeled samples, collection issues, or transcription mistakes can all affect the calculation. If the result does not fit the patient’s status or the surrounding labs, repeating the test may be appropriate.
The broader acid-base disorder pattern also matters. A person may have a combined disorder where the anion gap seems normal even though another problem is occurring. In the same way, a high result may need more than one follow-up test to identify the cause. That is why the calculator should be used as part of a more comprehensive interpretive workflow.
Request medical review if the result is significantly abnormal, if there are symptoms such as vomiting, confusion, rapid breathing, or severe illness, or if there is concern for conditions like toxic alcohol exposure, ketoacidosis, renal failure, or lactic acidosis. The calculator can suggest a problem, but a clinician is needed to evaluate the full picture and decide on next steps.
FAQs About the Anion Gap Calculator
What values do I need for an anion gap calculator?
You usually need sodium, chloride, and bicarbonate. Some calculators also ask for potassium. If the tool includes albumin correction, you may also need serum albumin. Use values from the same blood chemistry panel whenever possible.
How is the anion gap calculated online?
An online anion gap calculator relies on a formula based on electrolyte concentrations. The most common version is sodium minus chloride minus bicarbonate. Some calculators include potassium, and some also provide albumin correction for a more precise corrected anion gap.
What is a normal anion gap result?
A normal anion gap result falls within the calculator’s or lab’s reference range. The exact normal range can vary by method and reference interval, so always compare the number to the range shown by the tool or on the laboratory report.
Why would I need to correct the anion gap for albumin?
Albumin is a major unmeasured anion. If serum albumin is low, the measured anion gap may appear falsely normal or low. Correcting for hypoalbuminemia can expose a more accurate corrected anion gap and improve interpretation.
What does a high anion gap mean?
A high anion gap often suggests metabolic acidosis from extra unmeasured acids. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The result should always be interpreted in clinical context and reviewed by a clinician when abnormal.