What exactly the Anion Gap Shows
The anion gap is a calculated value based on common electrolytes in a routine chemistry panel. It helps clinicians detect hidden acids in the blood and understand whether a patient may have an acid-base disorder. The most common inputs are serum sodium, serum chloride, and serum bicarbonate, which are measured as part of regular serum chemistry testing.
At its core, the anion gap shows the difference between positively charged and negatively charged particles in the bloodstream. Because routine lab tests do not measure every ion, the result provides an estimate of the “missing” or unmeasured substances, often described as an anion difference or anion deficit. This makes it a helpful diagnostic tool when reviewing a possible metabolic derangement.
The buffer system in blood works steadily to keep pH stable. When acids accumulate, the anion gap can rise, especially when there are more unmeasured anions present. Interpreting the number correctly requires more than learning a formula. It requires considering the surrounding clinical picture, the patient’s symptoms, and the broader laboratory correlation.
The way the Anion Gap Calculator Functions
An anion gap calculator relies on a straightforward calculation formula based on standard lab values. In its most common form, it subtracts chloride and bicarbonate from sodium. Many calculators also allow adjustment for albumin, since albumin is a major unmeasured anion and can significantly influence the result.
The basic calculation is typically:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Because different laboratories may use slightly different methods and instruments, the reference range may vary. That is why an anion gap calculator should be used as a guide rather than a stand-alone diagnosis. The same result may be interpreted differently depending on the lab’s assay, the patient’s albumin level, and whether the clinical concern is metabolic acidosis or a different acid-base condition.
When albumin is low, the calculator may also provide a corrected value. This helps compensate for a lower baseline anion gap caused by reduced protein concentration. In practice, the calculator supports interpretation by turning raw lab values into a more clinically meaningful estimate.
Typical Anion Gap versus Increased Anion Gap
A standard anion gap usually implies that bicarbonate loss is being replaced by chloride, creating a no-gap or hyperchloremic pattern. A high anion gap, on the other hand, indicates the presence of excess acids or other unmeasured substances in the blood. This distinction is central to the evaluation of metabolic acidosis.
The exact normal range depends on the laboratory and whether the calculation includes potassium. Many clinicians think of a typical normal range as roughly within the low-to-mid teens, but the key point is to compare the value with the patient’s own lab standard rather than rely on a single universal cutoff.
A normal result does not always mean the patient is well, and a high result does not automatically mean a dangerous illness is present. The pattern should be interpreted alongside the bicarbonate level, pH if available, and the patient’s symptoms. That is where careful clinical interpretation is essential. In short:
- Normal anion gap: frequently suggests bicarbonate loss or chloride gain. High anion gap: commonly indicates acid accumulation from an underlying disease process.
Both patterns can appear in the same patient over time, especially when treatment changes the underlying acid-base balance.
Understanding a Low Anion Gap
A low anion gap is less common than a high one, but it should not be dismissed. The primary explanation is hypoalbuminemia, since albumin contributes substantially to the unmeasured anions that affect the result. When albumin decreases, the reported anion gap may also drop, even if no new acid-base problem exists.
Another important cause is laboratory error, sometimes written as lab error. Because the anion gap is derived from multiple lab values, any issue with sodium, chloride, or bicarbonate measurement can create a misleading result. If the number is unexpected, repeating the panel is often the initial practical step.
Paraproteinemia is another classic cause. In some protein disorders, abnormal positively charged proteins can reduce the anion gap. This does not mean paraproteinemia is the leading cause, but it is important when the low value is ongoing and unexplained. Other contributors may include unusual medications or analytical interference, but albumin, error, and paraprotein disorders are the key categories to keep in mind.
In a patient with a low anion gap, ask whether the finding is real, whether the serum albumin level is low, and whether the rest of the chemistry panel suggests a true metabolic issue.
Causes of High Anion Gap Metabolic Acidosis
A elevated anion gap is often a clue to acid buildup from increased acid generation or limited acid elimination. The major causes are often classified by mechanism, and the most clinically important include elevated lactate, ketone accumulation, kidney failure, and toxic exposures.
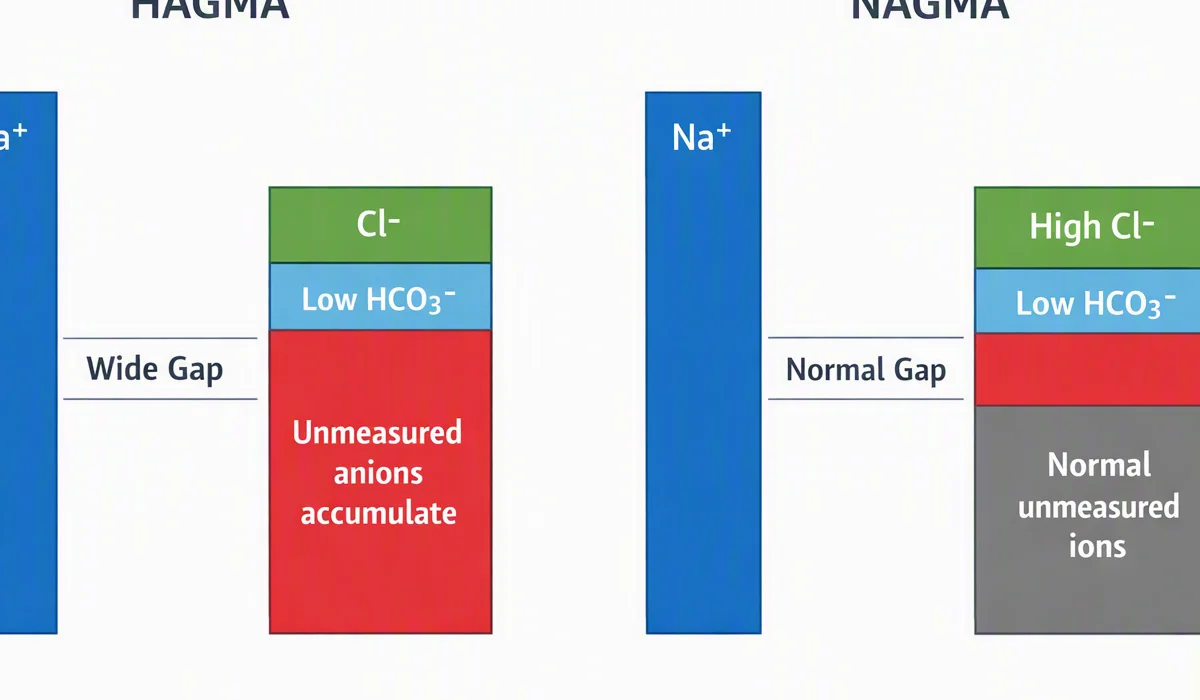
Lactate accumulation occurs when lactate accumulates, usually because of inadequate oxygen delivery to tissues, shock, severe illness, or impaired metabolism. Ketoacidosis may be related to diabetes, fasting, alcohol use, or other states that increase ketone production. Renal failure can lead to retention of organic acids that the kidneys would normally clear. Poisoning agents and drug exposures can also generate a high anion gap pattern by introducing acids that are not directly measured or interfering with metabolism.
Knowing the underlying physiology helps narrow the differential diagnosis. The number itself does not tell you the cause; it only signals that unmeasured acids are likely present. That is why the anion gap is best used as part of diagnostic evaluation rather than in isolation.
Key groups to consider include:
- Lactic acidosis from hypoperfusion, sepsis, or severe physiologic stress. Ketoacidosis from diabetes, starvation, or alcohol-related states. Renal failure with retention of acid load. Poisoning agents or medications that trigger or mimic a metabolic acidosis.
A high result should trigger a careful review of symptoms, vital signs, medication exposures, and other lab values that indicate severity and urgency.
Adjusted Anion Gap and Albumin Adjustment
The modified anion gap adjusts the measured value for the influence of albumin. This is essential because albumin adjustment can reveal a concealed acid-base problem that a raw result might miss. Since serum albumin is a major undetected anion, low albumin can make the anion gap appear within range even when excess acids are present.
Albumin correction improves acid-base balance interpretation by estimating what the anion gap would be if albumin were typical. Many calculators apply this automatically. When they do not, clinicians may perform a correction formula based on the patient’s albumin level. The result is a more reliable corrected value that more accurately reflects the actual metabolic state.
This matters most when the patient is sick, malnourished, has chronic inflammation, or otherwise has a low albumin concentration. In those settings, a seemingly normal uncorrected gap may be misleading. If the clinical picture suggests acidosis, the corrected result can uncover a unrecognized problem and support more rapid decision-making.
Albumin adjustment does not replace the rest of the workup. It is a fine-tuning that improves assessment and helps connect the chemistry panel to the broader pathophysiology.
Step-by-Step Interpretation Process
Understanding an anion gap result is most effective as a series rather than a brief review at the number. The goal is to relate the calculator output with the patient’s actual condition and determine whether the result fits an acid-base disorder.
A useful approach includes these steps:
- Examine the serum sodium, serum chloride, and serum bicarbonate values used by the calculator. Assess the result with the lab’s reference range. Check the bicarbonate level for evidence of metabolic acidosis. Assess the albumin value and consider albumin correction if needed. Use the arterial blood gas when available to confirm pH and respiratory compensation. Combine the result with clinical assessment, including symptoms, medications, and medical history.
An arterial blood gas can clarify whether the chemistry panel reflects true acidemia, compensation, or a mixed disorder. The blood gas also helps differentiate isolated chemistry abnormalities from a clinically important acid-base disturbance. In many cases, the best interpretation comes from pairing the calculator with the blood gas, exam findings, and serial lab values.
Remember that the anion gap is a screening test, not a final diagnosis. It suggests a problem, but the surrounding data determine what that problem is.
When to Reassess Lab Results or Seek Urgent Evaluation
Not every abnormal result requires urgent action, but some AG units mEq/L mmol/L conversion situations call for retesting or rapid response. If the result seems discordant with the patient’s condition, if there is concern for dangerous values, or if the calculation may have been affected by a collection problem, rechecking the chemistry panel is appropriate.
Look closely at the full clinical picture. Concerning signs may include altered mental status, increased breathing rate, profound weakness, persistent vomiting, chest discomfort, or signs of shock. These findings can indicate serious metabolic derangement and should trigger prompt evaluation. When symptoms are severe, or when the patient appears unstable, emergency evaluation is warranted.
Repeat testing is also useful when a low anion gap may reflect testing error, or when a corrected calculation is needed because albumin was not included. If the abnormality persists, the next step is usually a deeper medical evaluation rather than simple observation.
In short, repeat the labs when the number is unexpected, the sample may be unreliable, or the clinical picture does not match the result. Obtain urgent evaluation when symptoms or associated findings suggest a potentially dangerous acid-base problem.
Frequently Asked Questions
What counts as a normal anion gap?
The expected range depends on the laboratory method and the way the calculation is performed. Many labs use a reference range in the low-to-mid teens, but the most accurate answer is the one listed by the testing facility. Always interpret the result in context with albumin, bicarbonate, and the rest of the chemistry panel.
How do you calculate the anion gap?
The standard calculation formula is serum sodium minus the sum of serum chloride and serum bicarbonate. An Anion Gap Calculator performs this automatically and may also provide a corrected value when albumin is low.
Why does reduced albumin influence the anion gap?
Albumin is a key unmeasured anion. When albumin falls, the measured anion gap can also drop, which may mask an underlying acid–base problem. That is why albumin correction is important when reading results in patients with hypoalbuminemia.
What causes a high anion gap?
The main causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, renal failure, and certain toxins. The appropriate next step is to correlate the chemistry findings with the symptoms, arterial blood gas, and the rest of the laboratory evaluation.
When should an abnormal anion gap be rechecked?
Recheck the result when it does not align with the clinical picture, when lab error is possible, or when the patient has alarming symptoms. Repeat testing is also appropriate if the result is near a decision threshold or if albumin was not measured and a corrected value is needed. If the patient is not stable or has critical findings, seek urgent assessment without delay.