Defining the Anion Gap?
The anion gap is a derived value from serum electrolytes that helps providers assess acid-base balance. It compares measured sodium with the measured anions chloride and bicarbonate to estimate the amount of unmeasured anions in the blood. In routine blood chemistry, this gives the anion gap a useful marker in a metabolic acidosis workup and a reliable part of patient assessment.
The basic idea is easy: the body keeps positive and negative charges in balance. When the gap is higher than expected, it can suggest excess acids or other unmeasured substances. That is why the anion gap is often used as a diagnostic tool in the evaluation of metabolic acidosis and other acid-base disorder patterns.
The most common anion gap equation is:
Anion gap = Sodium - (Chloride + Bicarbonate)
This calculation incorporates values from an electrolyte panel and gives a lab result that must always be interpreted in context. Because different laboratories may use slightly different measurement methods and normal values, the expected reference range can differ.
How come Modify the Anion Gap for Albumin?
Albumin is the main unmeasured anion in plasma, so it has a significant effect on the anion gap. When a patient has hypoalbuminemia, the uncorrected anion gap can look spuriously normal or only mildly elevated even when significant acids are present. This is why the anion gap is often corrected for albumin.
Low albumin decreases the baseline gap because there are a smaller number of negatively charged proteins contributing to the measured balance. That can hide a significant metabolic acid load and reduce the sensitivity of the test for detecting metabolic acidosis. In other words, a patient with low albumin may have a “normal” gap on paper but still have an underlying high anion gap process.
Correcting the result enhances anion gap interpretation and supports better clinical significance. It helps distinguish true normal anion gap states from masked high-gap states in the setting of low albumin. This is especially important during critically ill patient assessment, where changes in albumin are common.
Corrected Anion Gap Formula and Computing Steps
The corrected anion gap modifies the observed gap for the patient’s albumin concentration. The precise albumin correction factor may vary by reference, but a typical approach is to add 2.5 mEq/L to the measured anion gap for every 1 g/dL albumin below 4.0 g/dL.
One common formula is:
Albumin-corrected anion gap = Measured anion gap + 2.5 × (4.0 - serum albumin in g/dL)
Example 1:
- Na = 140 Cl = 104 Bicarbonate = 20 Albumin = 2.0 g/dL
First calculate the anion gap:
140 - (104 + 20) = 16
Then apply the albumin correction:
2.5 × (4.0 - 2.0) = 5
Albumin-corrected anion gap = 16 + 5 = 21
That corrected value suggests a increased burden of unmeasured anions than the unadjusted result might imply.
Sample 2:
- Sodium = 138 Cl = 109 Bicarbonate = 24 Serum albumin = 1.8 g/dL
138 - (109 + 24) = 5
2.5 × (4.0 - 1.8) = 5.5
Albumin-corrected anion gap = 10.5
Although the uncorrected value is near normal, the albumin-adjusted result stays within or close to a usual reference range depending on the lab. This is why albumin correction matters so much in routine clinical testing.
To compute the anion gap correctly, follow these steps:
- Collect sodium, chloride, and bicarbonate from the electrolyte panel. Calculate the measured anion gap using the anion gap equation. Review the serum albumin level. Enter the albumin correction factor if albumin is low. Compare the corrected result with the lab’s reference range.
Remember that some institutions use slightly different formulas or cutoffs, so the final interpretation should always account for the local reference range and method used by the medical calculator or laboratory system.
How to Operate an Anion Gap Calculator
An Anion Gap Calculator is a clinical calculator that helps clinicians swiftly calculate anion gap and provide albumin-adjusted interpretation. It is especially useful when checking a blood chemistry panel during a metabolic acid workup, because it minimizes arithmetic errors and accelerates decision-making.
To work with a calculation tool correctly, input the relevant lab values exactly as reported:
- Sodium Chloride Bicarbonate Albumin
Some tools may ask for the serum bicarbonate directly, while others use total CO2 as a proxy depending on the lab format. Always make sure the values originate from the same electrolyte panel and reflect the same sample to avoid inconsistency in the lab result.
When using an Anion Gap Calculator, the output usually shows:
- Measured anion gap Albumin-adjusted or corrected anion gap Reference range comparison
This aids clinical interpretation, especially when hypoalbuminemia is present. A calculator can also make it simpler to compare repeated results over time and track trends in acid-base disorder management.
That said, the calculation tool does not take the place of judgment. The calculator provides a number, but the clinician must decide whether the result aligns with the patient’s overall picture, including symptoms, medications, and other laboratory findings.
How to Interpret a Elevated or Expected Corrected Anion Gap
A high anion gap metabolic acidosis implies that unaccounted-for acids are gathering in the circulation. If the corrected value is above normal, the next step is to determine the cause of the acid load. Common causes include lactic acidosis, ketoacidosis, renal dysfunction, and toxin exposure.
If the corrected anion gap is within range, the patient may have a normal anion gap pattern, often associated with bicarbonate loss or chloride gain rather than surplus unmeasured acids. This is frequently seen in some forms of diarrhea, renal tubular disorders, or saline-related acid-base changes. Even then, the overall clinical context remains crucial.
Here is a practical way to think about the result:
- High corrected gap: think about high anion gap metabolic acidosis and investigate unmeasured anions. Normal corrected gap: consider normal-gap processes and assess chloride and bicarbonate shifts. Borderline result: recheck albumin, repeat testing if needed, and look for mixed disorders.
In clinical practice, lactic acidosis may occur with shock, hypoperfusion, or severe illness, while ketoacidosis is often linked to diabetes, starvation, or alcohol use. Both can increase acid production and elevate the corrected gap. These patterns are a major part of anion gap interpretation because they inform urgent evaluation and treatment.
Typical Causes of an Elevated Corrected Anion Gap
An abnormal corrected anion gap can suggest several relevant disorders. The differential diagnosis depends on whether the corrected value is increased, unchanged, or unexpectedly decreased. In the context of a metabolic acidosis workup, the most important causes https://anion-gap-widget991.opalvector.com/posts/anion-gap-calculator-to-assess-metabolic-acidosis-analysis include renal failure, uremia, toxic alcohols, and salicylates.
Renal failure can increase the gap because the kidneys cannot remove acids normally, allowing metabolic acids to accumulate. As kidney function declines, retained acids contribute to uremic patterns and a widening gap.
Uremia is a typical cause of high-gap acidosis due to retained organic acids and other unmeasured anions. In advanced kidney disease, this may be a prominent driver of abnormal blood chemistry values.
Toxic alcohols such as methanol or ethylene glycol can lead to a dangerous high-gap state by creating acidic metabolites. When suspected, the clinical picture often includes neurologic changes, visual symptoms, or kidney injury, but the lab pattern may be the first clue.
Salicylates can create mixed acid-base patterns and may raise the anion gap through increased organic acids. The resulting picture can be complicated, so correlation with history and additional testing is necessary.
Other causes of elevated corrected values may include:
- Elevated lactate from poor perfusion or severe illness Acid buildup from ketones from diabetes, fasting, or alcohol-related states Poisoning and medication-related acidosis Marked kidney impairment with acid buildup
Understanding these trends improves diagnostic interpretation and supports appropriate next steps when the lab result is abnormal.
Limitations, Errors, and Clinical Considerations
The corrected anion gap is valuable, but it is not perfect. One major drawback is lab error. Small errors in sodium, chloride, or bicarbonate can meaningfully change the final result, especially when the gap is only modestly abnormal. Rechecking values may be appropriate when the pattern does not fit the clinical picture.
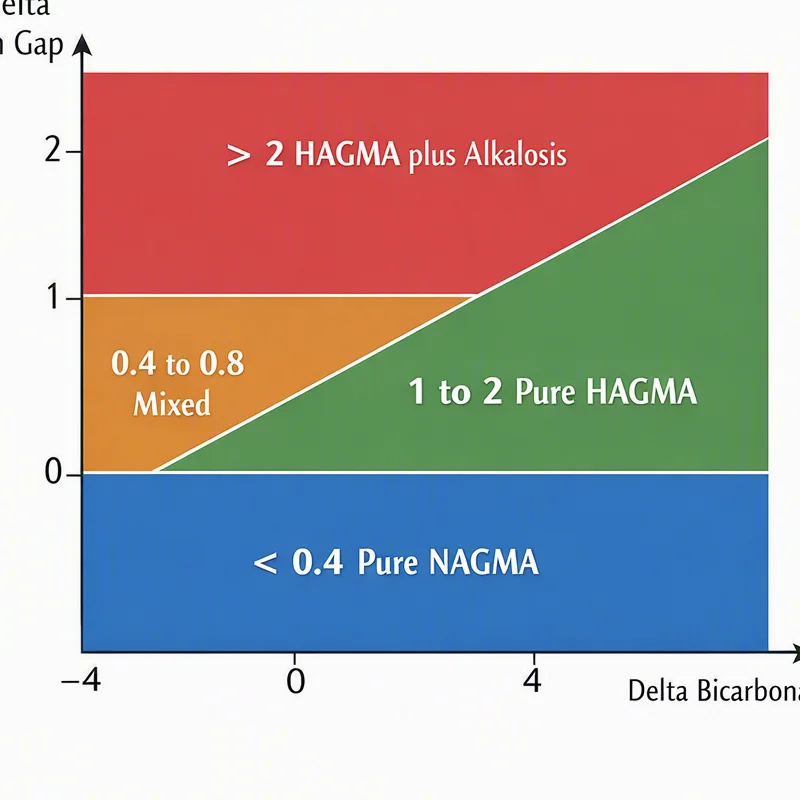
Another key concept is the delta gap, which evaluates the rise in the anion gap with the fall in bicarbonate. This can help detect mixed acid-base disorders. For instance, a high gap with a less-than-expected bicarbonate drop may suggest an additional metabolic alkalosis, while the reverse can suggest a simultaneous non-gap process.
Mixed acid-base disorders are frequent in sick patients, and the corrected anion gap should be used as part of a more comprehensive clinical interpretation rather than as a isolated answer. The result should be considered alongside pH, pCO2, lactate, ketones, kidney function, and medication history.
Additional pitfalls include:
- Relying on outdated or mismatched lab values from different collection times Failing to account for albumin when it is clearly low Choosing the wrong correction factor for the lab method Missing a normal anion gap process masked by other abnormalities
Good clinical interpretation requires the full picture. The corrected anion gap is a guide, not a diagnosis. It should support the broader assessment of the patient, especially when symptoms, blood gas data, and biochemical markers point in different directions.
Frequently Asked Questions: Adjusted Anion Gap Questions
How do you determine corrected anion gap?
To begin, determine the anion gap using sodium minus the sum of chloride and bicarbonate. After that adjust it for albumin using an albumin correction factor, commonly 2.5 mEq/L for each 1 g/dL that albumin is below 4.0 g/dL. This results in an albumin-adjusted result that is more accurate in patients with low albumin.
What is considered the albumin correction factor for anion gap?
A commonly used albumin correction factor is 2.5 mEq/L per 1 g/dL decrease in albumin below 4.0 g/dL. Some labs or references may use slightly different values, so the exact method should match the reference range and the calculation tool being used.
Why can low albumin lower the anion gap?
Albumin is a major unmeasured anion in blood. If albumin is reduced, fewer negative charges are present, so the measured anion gap decreases. This may make a high-gap disorder appear less obvious unless the result is corrected for albumin.
What can a high corrected anion gap mean?
A high corrected anion gap usually means there are excess unmeasured acids in the blood. Common causes include high anion gap metabolic acidosis from lactic acidosis, ketoacidosis, renal failure, uremia, toxic alcohols, or salicylates. This is a clue that further diagnostic interpretation is needed.
When is best to use an anion gap calculator be used?
An Anion Gap Calculator should be used whenever you need to calculate anion gap quickly and accurately, especially if albumin is low or the acid-base disorder is not straightforward. It is especially helpful during metabolic acidosis workup, routine electrolyte panel review, and any situation where corrected interpretation may change the clinical significance of the lab result.