What’s the anion gap?
The anion-gap value is a calculated measurement used to aid in interpret an acid-base disorder from a basic electrolyte test panel. It compares with the main measured cations and anions in serum electrolytes, usually using sodium, chloride, and bicarbonate. In many cases, potassium may also be included, but the most common clinical formula focuses on sodium, chloride, and bicarbonate because potassium contributes less to routine interpretation.
A common way to calculate the anion gap is:
Anion gap = Sodium - (Chloride + Bicarbonate)
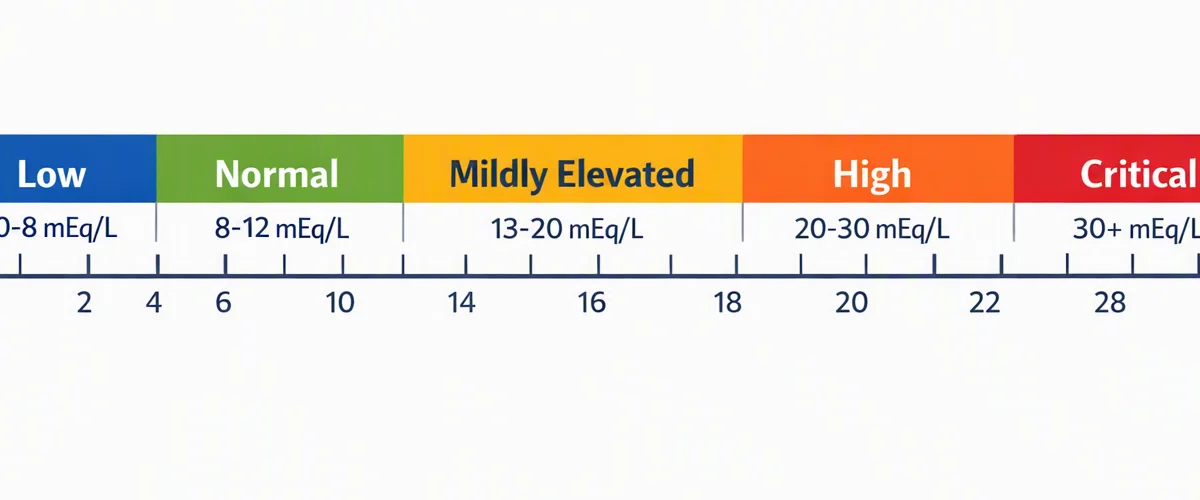
This estimate helps identify whether there are unmeasured anions in the blood. A higher-than-normal result can suggest metabolic acidosis, especially high anion gap metabolic acidosis, while a decreased value may reflect low albumin, laboratory variation, or other factors. Because the result is a derived number, the interpretation depends on the measured value, the normal range used by the laboratory, and the overall clinical assessment.
An anion gap calculator can speed up this process by structuring the formula and helping clinicians assess the electrolyte panel consistently. Still, the calculator is only a screening aid. The interpretation always depends on the full clinical picture, including serum bicarbonate, serum albumin concentration, and other laboratory values.
Why does hypoalbuminemia alter the anion gap?
This protein is the most important hidden charge in plasma. It has a slight negative charge, so when albumin drops, the measured anion gap often declines too. This is why hypoalbuminemia can conceal a clinically important metabolic disturbance. A patient may appear to have a normal or only mildly elevated anion gap even when acid accumulation is present.
The mechanism is simple: less albumin means fewer negatively charged proteins contributing to the gap. Because the body must maintain acid-base balance, other ions move to support electrical neutrality. The result is that the measured anion gap can underestimate the true burden of unmeasured acids.
This is especially important in patients with low albumin, because a normal anion gap does not always mean normal acid-base interpretation. In fact, hypoalbuminemia can conceal high anion gap metabolic acidosis. That is why the albumin-adjusted approach enhances diagnostic accuracy and helps clinicians avoid missing a serious condition.
In practical terms, the lower the albumin level, the more likely the measured gap will be reduced. The correction is intended to provide a more realistic estimate of the patient’s acid-base balance by accounting for the missing negative charge from albumin.
How do you calculate the anion gap for low albumin?
The adjusted anion gap uses a calculation formula that modifies the measured anion gap for the patient’s serum albumin. The purpose is to determine what the anion gap would be if albumin were in the normal range.
Corrected anion gap = Measured anion gap + 2.5 mEq/L for each 1 g/dL albumin below normal
In other words, the albumin correction factor is commonly applied as 2.5 mEq/L per 1 g/dL albumin below the reference range. Many clinicians use an anion gap calculator to accelerate the calculation and decrease error, especially when multiple laboratory values must be checked quickly.
Here is the basic calculation logic:
- To begin, calculate the measured anion gap from sodium, chloride, and bicarbonate. Next, determine the serum albumin concentration. Assess the albumin level with the laboratory reference range. Apply the correction formula using 2.5 mEq/L per 1 g/dL albumin below normal. Interpret the corrected anion gap in the context of the patient’s clinical context.
This is especially useful when assessing metabolic acidosis because the corrected value can reveal a high anion gap that the measured value may have missed. The process enhances interpretation and supports more accurate clinical assessment.
For example, if the measured anion gap is normal but the albumin is low, the albumin-adjusted anion gap may actually be elevated. That change can alter diagnosis, management, and urgency.
What is the albumin correction coefficient in 2026?
In 2026, the most widely used albumin correction factor remains 2.5 mEq/L per 1 g/dL albumin. This value is widely used because it provides a pragmatic and medically useful adjustment for laboratory interpretation.
The usual reference range for albumin varies by laboratory, but many sources use approximately 4.0 g/dL as a reference point for correction. If a patient’s serum albumin concentration is under that reference range, the corrected anion gap is adjusted upward by the amount expected to offset the lost negative charge.
An example of the correction method:
Corrected anion gap = Measured anion gap + 2.5 × (4.0 - serum albumin in g/dL)
This albumin correction is not perfect, but it is a helpful clinical approximation. It improves laboratory interpretation, especially when the goal is to identify masked high anion gap metabolic acidosis. For that reason, the correction coefficient remains useful as a practical standard in 2026.
Different institutions may use somewhat different formulas or thresholds, so clinicians should always consider local reference range policies. Even so, the core principle remains the same: low albumin reduces the measured anion gap, and correction enhances acid-base interpretation.
When should you calculate a corrected anion gap?
You should work out a corrected anion gap when hypoalbuminemia is present and acid-base interpretation matters. This is especially useful in metabolic acidosis, where a normal measured anion gap may be misleading.
Common situations include:
- Suspected high anion gap metabolic acidosis Critical illness with low albumin Renal failure with possible retained acids Unexplained changes in serum bicarbonate Mixed acid-base disorder patterns
Critical illness often involves inflammation, malnutrition, fluid shifts, and reduced albumin synthesis, all of which can lower albumin. In those settings, relying only on the measured value may minimize the severity of the metabolic disturbance. The albumin-adjusted result can provide a better screening tool for hidden acid accumulation.
Renal failure is another important example because reduced acid clearance can increase the anion gap. If albumin is low at the same time, the measured value may look less abnormal than it truly is. In such cases, a corrected anion gap can improve diagnostic accuracy and support further evaluation.
In general, the more abnormal the serum electrolytes and albumin are, the more useful the correction becomes. That does not mean every patient needs the calculation, but it is especially helpful when the clinical context suggests a significant metabolic disturbance.
What are the drawbacks of the corrected anion gap?
The corrected anion gap is helpful, but it is not absolute. One limitation is testing variation. Different analyzers, assay methods, and reporting conventions can affect sodium, chloride, bicarbonate, and albumin values. Small shifts in laboratory values may alter the calculated result.
Another limitation is that mixed acid-base disorders can cloud interpretation. For example, a patient may have metabolic acidosis and metabolic alkalosis at the same time. In that case, the anion gap alone may not fully show the underlying physiology. The corrected anion gap helps, but it should not replace full clinical assessment.
Albumin level also matters because the formula assumes a standard relationship between albumin and the gap. That relationship may not hold perfectly in every patient. Severe illness, paraproteinemia, unmeasured ions, and unusual electrolyte patterns can all affect the final reading.
For that anion gap calculator with albumin reason, clinicians should interpret the result in clinical context rather than treating the corrected number as absolute. The correction improves the estimate, but it does not eliminate uncertainty. The best use of the calculation is as part of a broader evaluation that includes symptoms, acid-base status, and the rest of the electrolyte panel.
In short, the corrected anion gap is most helpful when used thoughtfully. It increases confidence, but it cannot replace bedside judgment, trend review, and attention to the patient’s overall condition.
Illustrations of corrected anion gap computations
Example calculations help make the concept more straightforward to apply. Below are practical illustrations using a measured anion gap, albumin in g/dL, and the standard correction factor.
Example 1:
Measured anion gap = 10 mEq/L
Serum albumin concentration = 2.0 g/dL
With a reference point of 4.0 g/dL, the albumin deficit is 2.0 g/dL.
Correction = 2.5 × 2.0 = 5.0 mEq/L
Corrected anion gap = 15 mEq/L
Clinical note: The measured value looked normal, but the corrected anion gap suggests a possible high anion gap process. That is a classic example of how low albumin can hide metabolic acidosis.
Example 2:
Measured anion gap = 16 mEq/L
Serum albumin concentration = 3.0 g/dL
Albumin deficit = 1.0 g/dL
Correction = 2.5 × 1.0 = 2.5 mEq/L
Corrected anion gap = 18.5 mEq/L
Interpretation: The corrected value is more obviously elevated and supports evaluation for high anion gap metabolic acidosis.
Example 3:
Measured anion gap = 8 mEq/L
Serum albumin concentration = 1.5 g/dL
Albumin deficit = 2.5 g/dL
Correction = 2.5 × 2.5 = 6.25 mEq/L
Corrected anion gap = 14.25 mEq/L
Clinical note: This result shifts from low-normal to potentially abnormal once hypoalbuminemia is accounted for. That change can materially affect diagnosis and management.
This highlights why an anion gap calculator can be so helpful in daily practice. It turns a quick formula into a reliable step in interpretation, especially when multiple laboratory values must be reviewed together.
FAQs about anion gap correction in hypoalbuminemia
What is the corrected anion gap in hypoalbuminemia?
The corrected anion gap in hypoalbuminemia is the calculated anion gap raised to account for low albumin. Because albumin contains negative charge, low albumin can make the measured value seem lower than it is. The corrected result gives a clearer estimate of the actual acid-base status.
How do you calculate anion gap correction for albumin?
First calculate the measured anion gap from sodium, chloride, and bicarbonate. Then add 2.5 mEq/L for each 1 g/dL of albumin below the usual reference level, often 4.0 g/dL. This correction formula is commonly used to produce an adjusted anion gap.
Why can low albumin lower the measured anion gap?
Low albumin lowers the measured anion gap because albumin is a primary unmeasured anion in serum. When albumin decreases, fewer negative charges are present, so the gap decreases. This can underestimate metabolic acidosis unless the value is corrected.
Which correction factor is used for albumin in 2026?
The commonly used albumin correction factor in 2026 is 2.5 mEq/L per 1 g/dL albumin below normal. This factor is frequently used for laboratory interpretation, although local reference range practices may vary.
When does a corrected anion gap more useful than the measured anion gap?
A corrected anion gap is more useful when hypoalbuminemia is present, particularly in metabolic acidosis, high anion gap metabolic acidosis, critical illness, renal failure, or any possible mixed acid-base disorder. In those settings, the measured value may underestimate the real abnormality, while the corrected result aids interpretation and clinical assessment.