What the Anion Gap Assesses
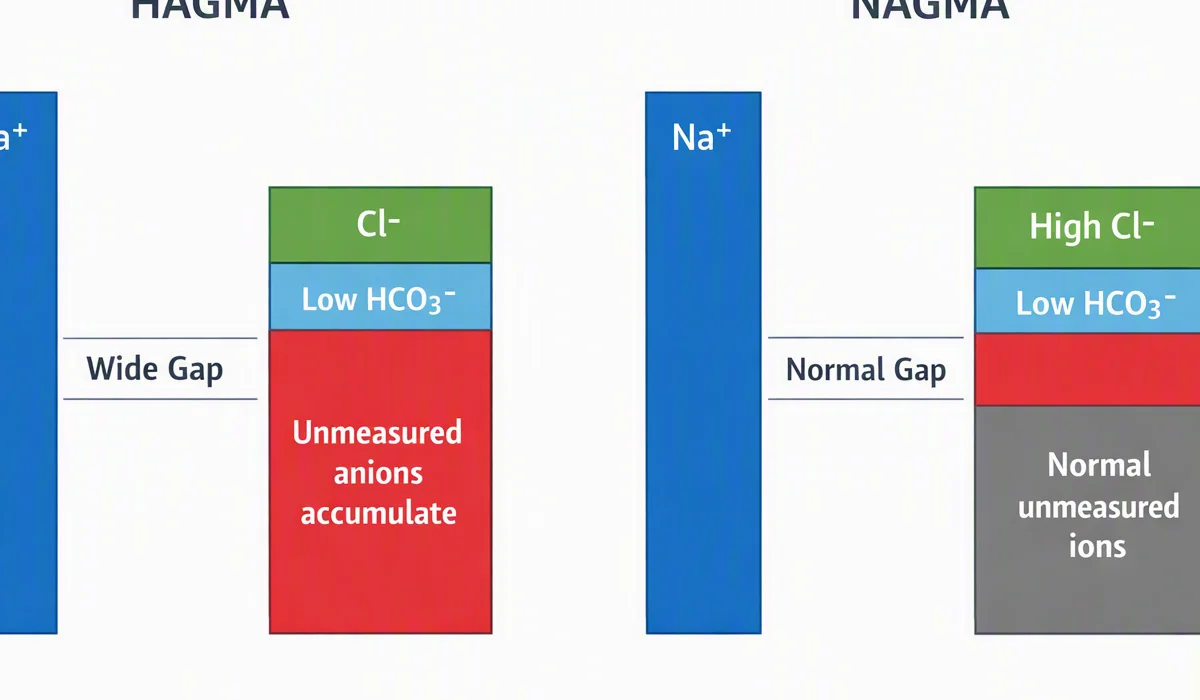
The anion gap is a derived result from serum electrolytes that supports clinicians assess acid-base balance. It is not a directly measured laboratory result; instead, it is a calculated value that estimates the difference between commonly measured cations and anions in blood chemistry. This makes it a useful diagnostic aid when reviewing laboratory results for possible acid-base disorder or electrolyte imbalance.
In everyday terms, the anion gap helps show whether there are unmeasured anions contributing to a metabolic problem. A change in the gap can point toward a metabolic derangement such as metabolic acidosis, especially when a patient’s symptoms and blood chemistry do not fully match the visible electrolyte values. This is why an anion gap calculator can be valuable during clinical assessment.
Although several formulas exist, the key idea remains the same: compare the main measured ions in the serum chemistry to estimate an “anion deficit.” The result supports clinical interpretation of acid-base status, but it should never be used alone. It works best alongside the patient’s history, other lab findings, and overall context.
Anion Gap Calculator: Inputs and Formula
An anion gap calculator typically uses sodium, chloride, and bicarbonate as the primary test inputs. For some calculations, potassium is included. In the potassium excluded formula, potassium is left out to streamline the calculation and match many modern clinical workflows.
The most common potassium-excluded formula is:
Anion gap = sodium - chloride - bicarbonate
This formula is based on the connection among the major measured ions in the electrolyte panel or basic metabolic panel. Because potassium is a minor component of extracellular electrolytes, many clinicians choose the potassium excluded approach for reliability and ease of use.
When using any calculator, ensure the inputs come from the same reference interval and collection time when possible. If the sodium, chloride, and bicarbonate values are from different draws or different sources, the formula output may not represent the patient’s current status accurately.
The calculator is most useful when you know what it is measuring: a balance between measured cations and anions. It is not a stand-alone diagnosis, but rather a way to assist interpretation of the patient’s serum electrolytes and possible acid-base disturbance.
How to Calculate Anion Gap Without Potassium
To complete the calculation formula correctly, enter the following values from the patient’s serum sodium, serum chloride, and serum bicarbonate:
- Use the serum sodium value. Remove the serum chloride value. Deduct the serum bicarbonate value.
The result is the potassium-excluded anion gap. For instance, if sodium is 140, chloride is 102, and bicarbonate is 24, the calculation is 140 - 102 - 24 = 14.
This method is simple, but the quality of the answer depends on accurate inputs. If any value is incorrect, the calculated value will be misleading. A calculator can reduce arithmetic errors, yet it cannot correct poor data entry or interpret unusual clinical situations on its own.
It is also important to remember that some laboratories report values using different units or decimal precision. Be sure the numbers you enter match the expected format for the calculator. A small mistake in reading the serum chemistry report can change the result enough to affect clinical interpretation.
In day-to-day practice, the potassium excluded version is valued because it is quick, easy to apply, and compatible with many blood chemistry workflows. It is especially useful when reviewing a full electrolyte panel or basic metabolic panel where sodium, chloride, and bicarbonate are immediately available.
Typical Anion Gap Range and Assessment
The expected range for anion gap differs by laboratory and by whether potassium is included. For the potassium-excluded approach, the expected reference range is often lower than formulas that include potassium. Because of this, always interpret the result using the lab’s stated reference range, not a generic value from memory.
A normal anion gap suggests that measured ions and unmeasured ions are in a balanced balance, at least from the standpoint of this calculation. That does not rule out illness, but it makes some causes of acidosis less probable. A elevated anion gap suggests an increase in unmeasured acids or other negatively charged substances, which can point toward a particular metabolic problem.
Interpretation should be tied to the broader overall assessment. For example, a patient may have a normal gap yet still have an acid-base disorder if there is a mixed process, recent treatment, or a lab artifact. Likewise, a mildly elevated gap may be clinically relevant in the right context or may reflect variation in lab results.
The key is not simply whether the result is above or below the number, but whether it fits the patient’s overall picture. The anion gap is best viewed as one part of a larger interpretation of acid-base status, including blood chemistry, symptoms, and other diagnostic findings.
Diagnostic Origins of an Abnormal Anion Gap
An elevated anion gap often indicates a metabolic acidosis state. In cases of high anion gap states, the body may be retaining acids faster than they can be eliminated or buffered. Typical examples include lactic acidosis, ketoacidosis, and renal failure.
Lactic acidosis can occur when tissues do not obtain enough oxygen, when there is serious illness, or when metabolic demand outpaces clearance. The accumulation of lactate elevates unmeasured anions, widening the gap. Ketoacidosis, observed in conditions such as uncontrolled diabetes or prolonged starvation, also elevates the gap because ketone bodies act as acid equivalents in the blood.
Renal failure can raise the gap because the kidneys are not as able to clear acids and other metabolic byproducts. This can produce a systemic acidosis with a expanded gap, especially when retained acids collect in the circulation. In these cases, the anion gap is a helpful marker of the body’s metabolic state, but it should be interpreted with other blood chemistry findings.
A normal anion gap can still be associated with relevant acidosis. For example, some forms of bicarbonate loss may not raise the gap, even though the patient has a genuine acid-base disorder. That is why the result must be interpreted in context rather than used in isolation.
When reviewing possible causes, think of the anion gap as a clue to the type of the acidosis, not just its presence. It helps differentiate patterns involving added acids from patterns involving bicarbonate loss or chloride gain, supporting more precise diagnostic interpretation.
Adjusting the Anion Gap for Albumin
Albumin is one of the key unmeasured anions in blood. When albumin is low, the measured anion gap may seem falsely normal or only mildly elevated, even when a clinically important acid-base problem exists. This is why hypoalbuminemia needs attention when interpreting results.
In patients with low albumin, an albumin correction or corrected anion gap may offer a more accurate view of the acid-base status. The exact correction method can vary by institution, but the goal is the same: revise the calculated value so it reflects the reduced contribution of albumin to the total anion burden.
If a patient has low albumin and a borderline gap, do not assume the result is reassuring. The corrected value may uncover a hidden anion gap elevation. This is particularly important when evaluating metabolic acidosis or other acid-base disorders in hospitalized or chronically ill patients.
Albumin correction is best applied as part of a broader clinical interpretation. It is not a substitute for reviewing symptoms, lactate, ketones, renal function, and the full serum chemistry. Still, when albumin is low, the corrected value can materially improve the usefulness of the anion gap calculator.
Common Calculation Mistakes to Watch For
One frequent mistake is a simple lab error or recording mistake. If sodium, chloride, or bicarbonate is entered inaccurately, the result can be inaccurate even if the arithmetic is accurate. Always confirm that the numbers entered into the calculator match the official laboratory results.
Another common issue is unit conversion. While most chemistry values are reported in standard units, some settings may use different formats or display formats. Mixing units can alter the calculation formula and produce an invalid answer. The same caution applies when entering values from different report systems or interfaces.
Misreading the reference range is also a problem. A value that is normal in one lab may be abnormal in another, especially if the lab includes potassium in its standard reference interval or uses a different method. Always use the lab’s own range when deciding whether the result is elevated, below normal, or normal.
Additional errors include using outdated values, mixing samples from different times, or forgetting that low albumin can mask an elevation. Since the anion gap is a calculated value, it can be affected by problems in the source data. Careful review of the serum electrolytes is important for accurate clinical interpretation.
When to Use a Potassium-Excluded Formula
The clinical use of the potassium-excluded approach is best suited when you want a fast, standardized estimate from a typical electrolyte panel or basic metabolic panel. Because potassium contributes very little to the total gap, excluding it often makes easier bedside or chart-based calculation without noticeably changing the overall clinical impression.
This version is especially practical when reviewing repeated serum chemistry values, because it makes comparison easier across time and across different clinical workflows. Many clinicians favor the potassium excluded formula for steadiness, particularly when evaluating metabolic acidosis, high anion gap states, or other patterns of acid-base balance.
That said, the most important reason to use the potassium-excluded formula is readability. It reduces calculation steps, avoids unnecessary dependence on potassium, and fits many standard diagnostic pathways. It can be a dependable diagnostic aid when used with the correct test inputs and interpreted in the context of the patient’s overall condition.
Use the formula when you need a useful estimate from readily available data, but remember that the result is only one piece of the puzzle. If the patient has hypoalbuminemia, possible lactic acidosis, suspected ketoacidosis, or worsening renal failure, the calculated gap should prompt deeper evaluation rather than end it.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the difference between measured cations and anions in blood chemistry. It helps clinicians assess acid-base balance, identify possible metabolic acidosis, and detect patterns suggesting excess unmeasured anions. It is a useful diagnostic aid, but it should always be interpreted alongside the patient’s symptoms and other laboratory results.
Why is potassium excluded from some anion gap formulas?
Potassium is omitted in some formulas because it adds relatively little to the overall formula and can make the equation more straightforward to use. The potassium excluded formula is generally accepted for routine clinical work and is often simpler to apply to an electrolyte panel or basic metabolic panel. Excluding potassium usually does not change the overall clinical interpretation in a meaningful way.
How do you calculate anion gap without potassium?
Use the calculation formula: sodium minus chloride minus bicarbonate. In other words, start with the serum sodium value, minus the serum chloride, and then subtract the serum bicarbonate. The NAGMA differential diagnosis result is the potassium-excluded anion gap. Be sure the values come from the same serum chemistry report whenever possible.
What does a high anion gap mean?
A high anion gap usually suggests that there are additional acids or other unmeasured anions in the blood. Common causes include lactic acidosis, ketoacidosis, and renal failure. A high result often points to a form of metabolic acidosis, but the full clinical picture is needed for accurate interpretation.
Should albumin be corrected when interpreting the anion gap?
Yes, especially if hypoalbuminemia is present. Because albumin is an important unmeasured anion, low levels can mask a true elevation in the gap. An albumin correction can produce a more accurate corrected anion gap and improve anion gap in chronic kidney disease clinical assessment. This is particularly important when the result seems normal but the patient still appears to have an acid-base problem.