How the Anion Gap Reflects
The anion gap is a useful way to evaluate the balance between electrolytes that are reported in routine blood testing and those that are not directly measured. Clinically, it helps assess acid-base balance and can indicate an acid-base disorder, especially when a patient may have an electrolyte imbalance.
In plain language, the anion gap reviews the main measured cations and anions in the blood. The result can reveal whether there are excess unmeasured anions, which often occurs in metabolic acidosis. That makes it a valuable screening metric and a helpful diagnostic tool in routine lab values review.
An anion gap calculator is designed to make this process fast and straightforward. Instead of calculating by hand, you enter the relevant serum electrolyte values and get an immediate formula result. This can support faster clinical interpretation and help direct further evaluation when the anion gap value is abnormal.
Formula and Calculation
The usual anion gap calculation uses Na, Cl, and bicarbonate:
Anion gap = Sodium - (Cl + HCO3)
In most routine calculations, blood sodium is the main positive component, while blood chloride and blood bicarbonate are the amounts removed from it. Since bicarbonate serves as an important buffer, the bicarbonate level strongly affects the final number and often indicates the body’s current acid base balance.
For instance, if serum sodium is 140, serum chloride is 104, and serum bicarbonate is 24, the calculation is:
140 - (104 + 24) = 12
That anion gap result is then compared with a normal range to help determine whether the result is typical or elevated. A correctly interpreted result can be especially useful during a acidosis workup, where identifying the pattern can limit the possible cause.
Even though the formula is simple, the meaning of the result depends on the overall clinical context. A single number does not diagnose a condition by itself, but it can signal when further testing is needed.
How to Operate the Anion Gap Calculator
Using an anion gap calculator is easy when you have the proper calculator input values. Input the 3 key lab results: serum sodium, serum chloride, and serum bicarbonate. The tool then runs the anion gap formula and delivers the calculated value immediately.
For the most precise result, use current and matching lab measurements from the osmolar gap vs anion gap in poisoning same blood chemistry panel. If values are entered from different draws, the calculation may be less reliable. As the anion gap is based on lab data, good input quality matters for accurate lab test interpretation.
- Provide serum sodium in the first field. Provide serum chloride in the second field. Input serum bicarbonate in the third field.
After calculating the anion gap, compare the result with the expected normal anion gap range used by the laboratory or clinical setting. A somewhat different reference range may apply depending on the method used by the lab. This is why the calculator should support, not replace, professional review of lab values.
While reviewing the output, pay attention to whether the formula result suggests a high anion gap, a low anion gap, or a value in the expected range. That classification helps guide next steps in evaluating possible acid-base or metabolic concerns.
Standard Anion Gap Range and Interpretation
The normal range for anion gap can vary somewhat by lab, but many clinical references treat values near 8 to 12 mEq/L to be expected when not adjusted for albumin. Some laboratories may use a slightly different lab range, so it is important to read the value alongside the reported lab standards.
A normal anion gap generally indicates that the balance between measured electrolytes and unmeasured ions is not significantly shifted. However, a normal result does not rule out all disorders. Some conditions can still be present even when the anion gap is normal, especially if the problem is unrelated to excess unmeasured anions.
A increased anion gap often signals excess acids in the blood and is commonly associated with metabolic acidosis. A low anion gap is less common but can be important because it may point to low albumin, lab issues, or unusual protein changes. Both abnormal patterns deserve attention in a full clinical interpretation.
In practice, the anion gap is one part of the larger picture. A number that appears just beyond the expected range should be reviewed with symptoms, history, medications, and other lab findings rather than interpreted alone.
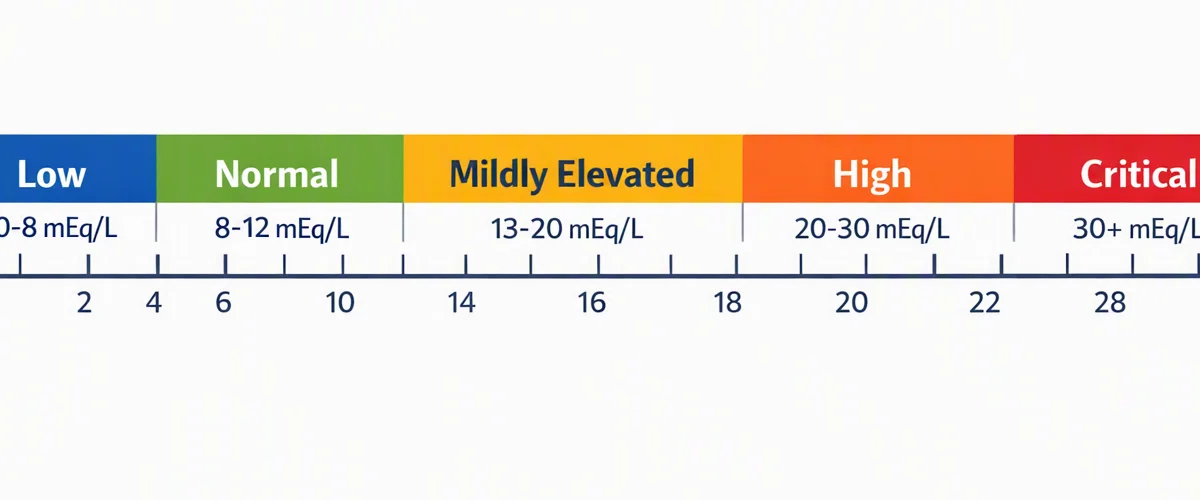
Typical Causes of a Elevated Anion Gap
A increased anion gap usually means there are extra untested anions in the blood, often because acids are piling up. This pattern is a key sign in metabolic acidosis and often calls for a broader metabolic acidosis workup.
One common cause is lactic acidosis, which can occur when the body produces too much lactate or cannot remove it effectively. Another important cause is ketone-related acidosis, which may develop when ketones build up during insulin deficiency, prolonged fasting, or other metabolic stress.
Kidney failure is another major cause because the kidneys may be unable to eliminate acids efficiently. As waste acids accumulate, the anion gap value can increase. Depending on the situation, the abnormal result may be accompanied by other changes in blood electrolyte results and a low bicarbonate concentration.
Other causes can occur as well, but these are among the most frequent and clinically important factors. When the calculator shows a high result, the pattern should be reviewed in combination with the patient’s symptoms, medications, and the broader chemistry panel.
Frequent Causes For a Low Anion Gap
A low anion gap can be rarer than an elevated one, but it can remain clinically meaningful. One frequent reason is hypoalbuminemia, because albumin is a major negatively charged protein in bloodstream. When albumin drops, the measured gap may also decrease.
Lab error should also be kept in mind, especially if the result doesn't match the clinical picture. Rechecking the sample or reviewing sample handling can help determine whether the value is real or due to an analytical issue.
Paraproteinemia is another important cause. In this condition, abnormal proteins can alter the balance of measured and unmeasured ions, changing the calculated result. Because of that, a low result may sometimes prompt more testing for protein abnormalities.
While a low result is often overlooked, it may indicate an underlying problem worth looking into. It is best understood alongside the rest of the blood chemistry panel and the patient’s overall health.
Modified Anion Gap and Albumin Correction
Since albumin contributes significantly to the anion gap, the raw number may underestimate the true acid burden when albumin is low. For this reason clinicians sometimes use a corrected anion gap with albumin correction.
This modification matters because albumin helps with protein binding and carries a negative charge. When albumin decreases, the measured gap can look lower even if there is still significant acidosis. Correcting the value can show a more accurate picture of acid-base status.
A corrected result is especially helpful when evaluating a possible acid-base disorder or when the patient has conditions associated with hypoalbuminemia. The goal is to avoid missing a hidden high anion gap simply because the raw number seems closer to normal.
Not all situations requires correction, but it should be considered whenever albumin is below normal or when the clinical picture and the calculated result do not match. In that setting, the corrected anion gap can enhance clinical interpretation and enable more accurate decision-making.
When to Seek Medical Evaluation
An abnormal anion gap is not always a crisis, but it should be taken seriously. If a person has alarming symptoms such as rapid breathing, confusion, severe weakness, vomiting, dehydration, or marked illness, medical evaluation may be needed promptly.
Because a elevated value can signal an important underlying problem, a clinician may request a blood chemistry panel along with other tests to determine the cause. This is especially true when there is concern for metabolic acidosis, renal failure, or another serious condition.
Seek emergency evaluation if symptoms are severe, worsening, or associated with fainting, difficulty breathing, altered mental status, or signs of severe dehydration. The calculator is a useful screening step, but it does not substitute for urgent care when the situation suggests a medical emergency.
For milder concerns, follow-up testing and clinician review can help determine whether the result was short-lived, related to lab error, or part of a larger pattern that needs treatment.
Frequently Asked Questions
How do you calculate anion gap from sodium, chloride, and bicarbonate?
Use the anion gap formula: sodium minus the sum of chloride and bicarbonate. In other words, anion gap = sodium - (chloride + bicarbonate). An anion gap calculator makes this easy by letting you enter the serum sodium, serum chloride, and serum bicarbonate values directly.
What is the normal range for anion gap?
The normal range differs by laboratory, but many references place it around 8 to 12 mEq/L. Always compare the result to the lab’s own reference range because methods and reporting standards can differ. A result inside the expected range is often considered a normal anion gap.
What means a high anion gap?
A high anion gap usually points to excess acids or unmeasured anions in the blood. Common causes include metabolic acidosis, lactic acidosis, ketoacidosis, and renal failure. The result should be read in the light of symptoms, other lab values, and the overall acid-base balance.
What can cause a low anion gap?
A low anion gap can be linked to hypoalbuminemia, lab error, or paraproteinemia. Low albumin is often common because albumin contributes negative charge in the blood. If the result is unexpected, repeating the test and reviewing the full blood chemistry panel can help identify the cause.
Should anion gap be corrected for albumin?
Yes, it often should be evaluated when albumin is low. The corrected anion gap can provide a more accurate picture because albumin affects the measured value through protein binding and its negative charge. Albumin correction is especially useful when evaluating an abnormal result during an acid-base disorder assessment.